Coffee · 9 of 64
Caffeine and Health: What the Evidence Says

Coffee is one of the most studied drinks in the world, and most of what is said about it is still wrong in one direction or the other: either it is a poison to be cut back, or it is a health food. The evidence is more useful than either. It says how much caffeine is in each cup, how long it stays, who should drink less, which brewing methods raise cholesterol and which do not, and what the long studies of hundreds of thousands of people can and cannot show.
This page is not medical advice. It reports what regulators and published studies say. Anyone with a heart condition, high cholesterol, a pregnancy, a medication that interacts with caffeine (some examples), or a child asking for an energy drink should ask their own doctor.
The short version
| Question | Answer |
|---|---|
| How much is safe? | Up to 400 mg a day for healthy adults (FDA, EFSA, Health Canada). The FDA puts that at “about two to three 12-fluid-ounce cups of coffee.” |
| In one sitting? | Up to 200 mg at once raises no safety concern for healthy adults (EFSA). |
| Pregnant? | 200 mg a day (EFSA; the American College of Obstetricians and Gynecologists says under 200 mg). Health Canada says 300 mg. |
| Children? | About 2.5–3 mg per kilogram of body weight a day at most. Energy drinks: none. |
| How much is in a cup? | Drip, 8 fl oz: about 95 mg. Single espresso: about 64 mg, but café shots have measured 51 to 322 mg. Instant: about 62 mg. Decaf: 2–15 mg. |
| Does dark roast have more caffeine? | No, not as usually brewed. Brewed the same way, dark roasts gave less caffeine in a 2024 study. Per gram of coffee actually dissolved, they gave a little more. The difference is small either way. |
| Does it dehydrate you? | No, at ordinary intakes: in a 2014 trial, three to four cups a day hydrated as well as the same volume of water. |
| Medicines, blood pressure, heartburn? | Two common drugs (fluvoxamine, ciprofloxacin) slow caffeine’s clearance sharply; coffee cuts the absorption of thyroid pills and of iron from a meal; caffeine raises blood pressure for a few hours but habitual coffee is not linked with high blood pressure; coffee is linked with slightly more reflux. |
| How long does it last? | Half of it is gone in 3 to 7 hours in most adults. Twice that on the contraceptive pill; longer still in pregnancy. |
| Is coffee good for you? | Large studies link 2–4 cups a day with lower death rates and less type 2 diabetes, liver disease and Parkinson’s disease. They are observational: they show an association, not proof of cause. |
| Cholesterol? | Unfiltered coffee raises LDL cholesterol; paper-filtered coffee does not. French press, Turkish and boiled coffee are the highest; espresso and moka are in between. A paper filter removes the cause. |
| Acrylamide, mould? | Both are real and both are regulated. California decided in 2019 that coffee needs no cancer warning. “Mould-free coffee” is marketing. |
| Decaf solvents? | Methylene chloride is still legal in US decaf at up to 10 ppm. A petition to ban it has been with the FDA since December 2023, still undecided as of October 2026. Swiss Water, CO₂ and ethyl-acetate decafs avoid it. |
| Withdrawal? | Real. Headache in about half of people who stop, starting 12–24 hours after the last cup and lasting 2 to 9 days. |
How much caffeine is in the cup
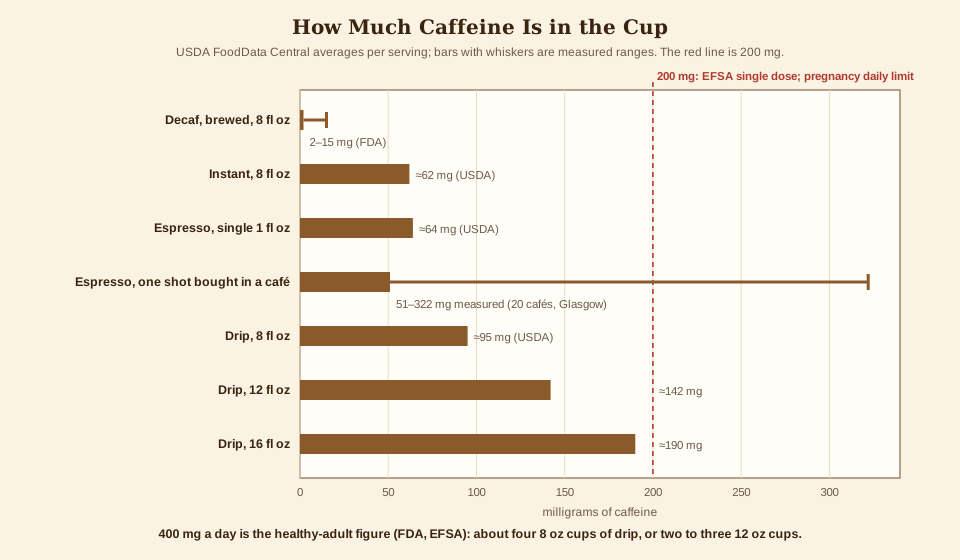
The averages come from the USDA’s FoodData Central database, which lists caffeine per 100 grams of the drink. Brewed coffee carries 40 mg per 100 g, espresso 212 mg, prepared instant coffee 26 mg and brewed decaf 1 mg. Multiplied out for ordinary servings:
| Drink | Serving | Caffeine | Note |
|---|---|---|---|
| Drip or pour-over | 8 fl oz (237 g) | about 95 mg | USDA average; real cups vary with the dose of coffee |
| Drip | 12 fl oz | about 142 mg | the FDA’s “cup” in its 400 mg sentence |
| Drip | 16 fl oz | about 190 mg | a medium at most chains |
| Espresso | 1 fl oz single | about 64 mg | USDA average |
| Espresso bought in a café | one shot | 51 to 322 mg | 20 cafés in Glasgow (Crozier and others, 2012) |
| Instant | 8 fl oz | about 62 mg | USDA |
| Decaf, brewed | 8 fl oz | 2 to 15 mg | FDA |
| Cold brew | 8 fl oz | no single figure | depends on the coffee-to-water ratio and how much the concentrate is diluted |
Two things in that table matter more than the averages.
A café espresso is not a fixed dose. The Glasgow study bought single espressos from twenty outlets and measured a six-fold spread, from 51 mg to 322 mg. Three of the twenty held more than 200 mg in one shot. The authors’ conclusion was that the old assumption of 50 mg in a strong cup “may be misleading.” A shop that pulls a double into every drink, or uses a robusta blend, sells a very different dose from one that does neither.
Robusta carries about twice the caffeine of arabica (The Bean), so a robusta blend, a Vietnamese phin coffee made with robusta, or a cheap instant holds more caffeine per gram than an all-arabica coffee. The USDA averages above do not say which species went in. Some coffees go the other way: a few naturally low-caffeine species and arabica varieties are on Beyond Arabica and Robusta.
Caffeine follows the dose of ground coffee. The coffee in the cup holds most of the caffeine that was in the grounds, so the number that sets the caffeine is how many grams went in. The Ratios page gives the weights. A strong 1:12 pour-over carries more caffeine than a 1:17 one from the same bag.
Cold brew
Cold brew has no standard strength, because some shops serve the concentrate and others cut it with water or milk. A 2017 study by Fuller and Rao (and the same authors’ 2018 follow-up on acidity) found that coarse-ground cold brew carried more caffeine than hot coffee made from the same grounds at the same ratio, that the caffeine finished extracting in 6 to 7 hours rather than the 12 to 24 that recipes ask for, and that the cold brew was not less acidic: its pH matched hot coffee. The “low-acid” claim on cold-brew labels is not supported by that measurement. The iced coffee page covers making it.
Dark roast does not have more caffeine
Two opposite myths circulate: that a dark roast is “stronger” in caffeine, and that a light roast has far more. A 2024 study by Lindsey and colleagues roasted the same green coffee to different levels and brewed each the same way. Brewed identically, the dark roasts gave less caffeine. Measured at the same extraction (the same share of the coffee dissolved into the cup), the dark roasts gave slightly more, because roasting burns off other material and leaves caffeine a bigger share of what is left. Caffeine itself barely changes in the roaster.
In practice: weigh the coffee and the difference is small. Measure by the scoop and a light roast gives a little more, because light beans are denser and a scoop holds more grams of them. The Roasting page explains what does change with roast level.
How much is too much
| Who | Daily limit | Source |
|---|---|---|
| Healthy adults | 400 mg | FDA; EFSA (“about 5.7 mg/kg”); Health Canada |
| Healthy adults, one sitting | 200 mg (about 3 mg/kg) | EFSA |
| Pregnant or breastfeeding | 200 mg | EFSA; ACOG (“less than 200 mg”) |
| Pregnant or breastfeeding | 300 mg | Health Canada |
| Children and teenagers | 3 mg/kg | EFSA |
| Children and teenagers | 2.5 mg/kg | Health Canada |
The two pregnancy figures disagree, and the lower one is the one most doctors in the US quote. The Columbia University Irving Medical Center summary of the American College of Obstetricians and Gynecologists’ guidance gives the under-200 mg figure. The largest review of coffee studies (Poole and others, BMJ 2017) found that pregnancy is the one place where the harmful associations survived adjustment for smoking: high coffee intake in pregnancy was linked with low birth weight (odds ratio 1.31) and pregnancy loss (1.46). Those are observational associations, but they are the reason every agency sets a lower limit in pregnancy.
Pure caffeine powder is the real danger. The FDA estimates that toxic effects such as seizures “can be observed with rapid consumption of around 1,200 milligrams of caffeine, or less than 1/2 teaspoon of pure caffeine.” No one reaches that from brewed coffee by accident. A bag of powder and a kitchen spoon can do it in one swallow.
How long it stays, and sleep
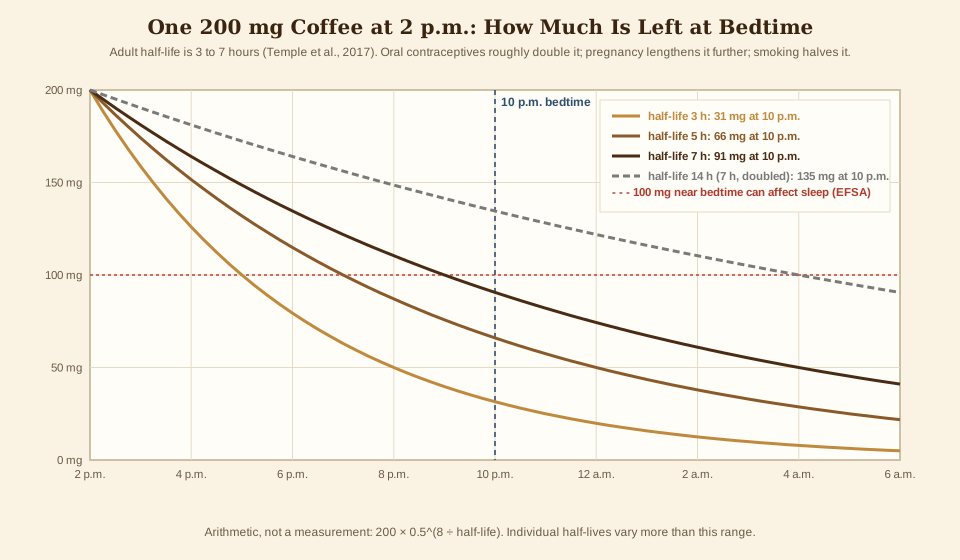
A half-life is the time the body takes to clear half of a dose. For caffeine in adults it is 3 to 7 hours, according to a 2017 review by Temple and colleagues, which also gives the things that change it:
| Situation | Effect on half-life |
|---|---|
| Healthy adult | 3 to 7 hours |
| Oral contraceptives | ”tend to double” it |
| Pregnancy | on average 8.3 hours longer, and up to 16 hours longer |
| Smoking | clearance roughly doubles, so the half-life roughly halves |
| Newborns | about 80 hours |
Caffeine peaks in the blood about two hours after drinking. The best-known sleep trial (Drake and others, 2013) gave people 400 mg at bedtime, 3 hours before, or 6 hours before. All three cut measured sleep by 1.1 to 1.2 hours, including the dose taken six hours earlier. EFSA notes that even 100 mg close to bedtime can affect sleep in some adults.
A practical rule from those numbers: with an average half-life, the last full cup belongs before early afternoon for a 10 p.m. bedtime. Someone on the pill, pregnant, or a slow metaboliser should stop earlier still.
Genes: fast and slow metabolisers
About 95% of caffeine is broken down by one liver enzyme, CYP1A2, and a common variant of its gene makes some people slow at it (Nehlig, 2018). Two big studies point in different directions, and both are worth knowing:
- In Costa Rica, Cornelis and others (JAMA, 2006) compared 2,014 people who had survived a first heart attack with 2,014 who had not. Among slow metabolisers, two to three cups a day went with a 36% higher risk (odds ratio 1.36) and four or more with a 64% higher risk (1.64). Among fast metabolisers there was no rise.
- In the UK Biobank, about half a million people, Loftfield and others (2018) found coffee drinkers had lower death rates whatever their genetic caffeine-metabolism score, up to eight or more cups a day.
The two studies measured different things (a first non-fatal heart attack, against death from any cause), so they do not cancel out. The fair reading: for most people coffee is not a heart risk, and the people for whom it might be are the slow metabolisers who drink a lot. A commercial genetic test can say which variant someone carries, but how a person sleeps after an afternoon coffee is already a rough guide.
What the big studies found
Most of what is known about coffee and long-term health comes from cohort studies: researchers ask a large group what they drink, then follow them for years and count what happens. The size is impressive. The weakness is that coffee drinkers differ from non-drinkers in other ways, and the studies can only adjust for the differences they measured.
The NIH-AARP study (Freedman and others, New England Journal of Medicine, 2012) followed 402,260 Americans aged 50 to 71 for up to 13 years. The raw numbers made coffee look dangerous, because coffee drinkers were more likely to smoke. Once smoking was accounted for, the picture reversed:
| Cups a day (men) | Risk of death, against none |
|---|---|
| fewer than 1 | 0.99 |
| 1 | 0.94 |
| 2 to 3 | 0.90 |
| 4 to 5 | 0.88 |
| 6 or more | 0.90 |
A risk figure below 1 means fewer deaths than among non-drinkers; 0.90 means 10% fewer. The study tables also use two close relatives: an odds ratio compares the odds of an outcome between two groups (used in case-control studies, such as the Costa Rica heart-attack study above), and a hazard ratio compares the rate at which it happens over the follow-up. For small risks all three read the same way: 1 is no difference, below 1 is fewer, above 1 is more.
The authors wrote: “Whether this was a causal or associational finding cannot be determined from our data.” That sentence belongs beside every headline about coffee and long life.
The other large results, all observational:
| Outcome | Finding | Source |
|---|---|---|
| Death from any cause | lowest at 3–4 cups a day: relative risk 0.83 | Poole and others, BMJ 2017, an “umbrella” review of 201 meta-analyses |
| Death from heart disease | 0.81 at 3–4 cups | same |
| Type 2 diabetes | 0.67 at 6 cups a day; decaf also linked with lower risk | Ding and others, Diabetes Care 2014, 28 studies, 1.1 million people |
| Cirrhosis of the liver | 0.56 for each extra 2 cups a day | Kennedy and others, 2016 |
| Liver cancer | 0.65 for each extra 2 cups; evidence graded “very low” quality | Kennedy and others, BMJ Open 2017 |
| Parkinson’s disease | 10.4 cases per 10,000 person-years in non-drinkers, 1.9 in men drinking 28 oz or more a day | Ross and others, JAMA 2000, 8,004 men followed 30 years |
| Heart disease, by type of coffee | decaf, ground and instant all linked with lower risk; lowest at 2–3 cups | Chieng and others, 2022, UK Biobank |
A relative risk of 0.83 means 17% fewer cases than in the comparison group over the study period. It does not mean a coffee drinker’s own risk falls by 17%.
What the decaf results suggest. If decaf is linked with less diabetes and less heart disease, caffeine cannot be the whole story. The UK Biobank authors drew that conclusion: the findings “suggest the importance of noncaffeine constituents.” The Parkinson’s result points the other way: the Honolulu authors concluded the link was with caffeine, not the rest of the coffee.
What would settle it. The BMJ review called for “robust randomised controlled trials.” None has run long enough to count deaths. Until then the honest summary is: coffee at ordinary amounts does not look harmful for most adults outside pregnancy, and it may help.
Cafestol: why unfiltered coffee raises cholesterol

Coffee beans contain two oily compounds, cafestol and kahweol (they are diterpenes), at about 1% of the bean’s weight. Hot water extracts them; a paper filter traps them. The researchers who identified them, Urgert and Katan (1997), summed it up: this “explains why filtered coffee does not affect cholesterol, whereas Scandinavian ‘boiled,’ cafetière, and Turkish coffees do.” (Cafetière is the British word for a French press.)
The clearest experiment (van Dusseldorp and others, 1991) gave volunteers six cups a day of boiled coffee, either as it was or poured through an ordinary paper filter. After 79 days, the unfiltered group’s total cholesterol had risen by 16 mg/dL (0.42 mmol/L) and its LDL (“bad”) cholesterol by 16 mg/dL (0.41 mmol/L) more than the filtered group’s; almost all of the rise was in LDL. The filtered coffee did nothing measurable to cholesterol.

How much cafestol each brew carries:
| Brew | Cafestol | Evidence |
|---|---|---|
| Boiled, Scandinavian, cowboy | highest | Urgert and Katan; van Dusseldorp |
| French press | high: the highest extraction of cafestol from light roasts | Zhang, Linforth and Fisk, 2012 |
| Turkish | high, though dark Turkish roasts extracted less | same |
| Moka pot | lower: the lowest extraction yield of the four methods tested | same |
| Espresso | small per cup: 1.2 to 2.3 mg of diterpenes in a 40 mL shot | Moeenfard and others, 2015 |
| Paper-filtered drip and pour-over | almost none | van Dusseldorp |
| Instant | no consistent effect in the Tromsø study | Svatun and others |
The Tromsø Study in northern Norway (21,083 people) put numbers on ordinary drinking. Three to five espressos a day went with total cholesterol 0.16 mmol/L (about 6 mg/dL) higher in men and 0.09 (about 3.5 mg/dL) in women. Six or more cups of boiled or plunger coffee went with 0.23 to 0.30 mmol/L higher (about 9 to 12 mg/dL). And a 20-year Norwegian study of 508,747 people (Tverdal and others, 2020) found that drinkers of filtered coffee had a lower death rate than non-drinkers (hazard ratio 0.85), while drinkers of unfiltered coffee did not do as well: 0.96 for men (95% confidence interval 0.91 to 1.01, no clear difference from non-drinkers) and 0.91 for women (0.86 to 0.96). Unfiltered coffee did not look harmful against no coffee; it simply lacked the filtered coffee’s advantage. The authors’ conclusion: “Unfiltered brew was associated with higher mortality than filtered brew.”
Metal filters do not count as paper. A French press screen, a gold-mesh cone, a percolator basket, a phin and an espresso basket all let the oils through. No study has measured cafestol in phin coffee, but on the evidence above it belongs with the unfiltered methods.
What it means at home
I own a French press, a pour-over kit and a phin, and the practical answer for any home drinker is simple:
- Normal cholesterol, a cup or two a day: brew any way you like. The effect is a few points of cholesterol, not a health event.
- High LDL, or a doctor watching it: make the daily coffee with a paper filter, and keep the French press, Turkish coffee or campfire pot for a weekend treat. Brewing through paper is the cheapest cholesterol change there is.
- Want the press body without the oils? Pour the finished press coffee through a paper filter. That is exactly the “boiled then filtered” coffee that did nothing to cholesterol in the 1991 trial.
What it means for a French-press shop
Around 1990 I owned a coffee and ice cream shop in Beaufort, South Carolina, and nearly all the coffee I sold was ground on site and brewed in French presses. A shop or stall built on presses is selling an unfiltered drink. That is no reason not to, and the brewing page explains why the press is worth it. Three things are sensible:
- Offer a paper-filtered option on the same menu: a pour-over or batch brew from the same bag. Customers watching their cholesterol will ask.
- Do not make health claims for either. A sign saying “filtered coffee lowers cholesterol” is a health claim and needs evidence a stall does not have; a menu line saying “paper-filtered” is a plain description (Labels and Certifications has the rules on health claims).
- Know the answer when a customer asks why their doctor told them to stop drinking press coffee. The answer is cafestol, and the paper fixes it.
Acrylamide and the California cancer warning
Acrylamide forms when foods rich in sugars and the amino acid asparagine are heated hard: toast, chips, fries and roasted coffee. In 2010 a group called the Council for Education and Research on Toxics sued coffee sellers under California’s Proposition 65, the state law requiring warnings for chemicals on its cancer list. A judge ruled against the coffee companies in 2014 and again in 2018, and for a while California coffee shops posted cancer warnings.
Then the state agency that runs Prop 65 changed its rules. In June 2019 it adopted a regulation stating that chemicals “created by and inherent in the processes of roasting coffee beans or brewing coffee do not pose a significant risk of cancer.” The courts upheld it in October 2022, and the California Supreme Court declined to hear the case in February 2023, ending twelve years of litigation (summary by Scali Rasmussen). By then the World Health Organization’s cancer agency, the International Agency for Research on Cancer (IARC), had already moved coffee, in 2016, from “possibly carcinogenic” to “not classifiable.”
The European Union deals with acrylamide by setting benchmark levels that food makers must work to stay under (Regulation 2017/2158): 400 µg per kilogram for roast coffee and 850 for instant. Roasted chicory, by comparison, has a benchmark of 4,000 — ten times higher (see Chicory and New Orleans Coffee).
Mould, mycotoxins and “mould-free” coffee
Green coffee that is badly dried or stored damp can grow moulds that make ochratoxin A, a mould toxin (mycotoxin). It is real and it is regulated: the EU’s maximum is 3.0 µg per kilogram of roasted coffee and 5.0 for instant (Regulation 2023/915).
Some brands sell coffee as “mould-free” or “mycotoxin-tested” and imply that ordinary coffee is making people tired or ill. No published study shows that drinkers of ordinary specialty coffee are harmed by mycotoxins, or that drinkers of the tested brands feel better for it. Buying from a roaster who buys carefully dried green coffee from a reputable importer is the real protection, and it is what any specialty roaster already does. The green coffee page covers buying it.
Decaf: four ways to take the caffeine out

All decaf is made from green coffee, before roasting. The beans are soaked or steamed to swell them, the caffeine is drawn out, and the beans are dried and sold to roasters. The four methods differ in what pulls the caffeine out:
| Method | What pulls the caffeine | Notes |
|---|---|---|
| Methylene chloride (“European” or “direct” method) | a chlorinated solvent | Widely used for US decaf; no public figure gives its exact share. Allowed in the US up to 10 ppm residue (21 CFR 173.255). |
| Ethyl acetate (“sugarcane” or “natural” decaf) | an ester found in fruit, often made from sugarcane | Café du Monde decafs this way. Can leave a faint fruity note. |
| Carbon dioxide (supercritical CO₂) | carbon dioxide under very high pressure | Large industrial plants; no solvent residue. |
| Swiss Water and other water processes | water already saturated with coffee’s other solubles, then carbon filters | Swiss Water in Delta, British Columbia, describes a “Green Coffee Extract” that lets only caffeine leave the bean, then traps it on carbon. |
None of these removes every trace. The FDA puts brewed decaf at 2 to 15 mg a cup, so ten cups of decaf can add up to a cup of regular coffee. Europe defines “decaffeinated” coffee extract as no more than 0.3% caffeine in the dry matter (Directive 1999/4/EC).

The methylene chloride question, as of October 2026
Methylene chloride (also called dichloromethane) causes cancer in animals, and the US Environmental Protection Agency banned most consumer and commercial uses of it in a rule signed in April 2024 and published on 8 May 2024. That rule does not reach food, which belongs to the FDA (CSPI).
| Date | What happened |
|---|---|
| December 2023 | The Environmental Defense Fund and four other petitioners asked the FDA to remove methylene chloride and three other solvents from the food-additive rules, under the Delaney Clause, which bars additives found to cause cancer in people or animals. |
| February–May 2024 | California’s AB 2066 was introduced to ban methylene-chloride decaf, was cut back to a labelling rule starting in 2027, and died in committee on 16 May 2024 (CalMatters). |
| 8 May 2024 | The EPA’s ban on most non-food uses was published. |
| 29 June 2026 | A reopened FDA comment period on the petition closed (Daily Coffee News). The FDA asked about practical phase-out timelines. |
| July 2026 | The FDA had not ruled (Barista Magazine). The National Coffee Association argued a ban would “defy science.” |
| October 2026 | Methylene chloride remains legal in US decaf at up to 10 ppm. |
Residues are measurable but small: a 1984 laboratory study found up to 4.0 ppm in fifteen decaf coffees (Page and Charbonneau). A buyer who wants to avoid the question entirely can: Swiss Water, CO₂ and ethyl-acetate decafs are widely sold and usually say so on the bag. A roaster selling decaf should know which process their importer used and print it on the label. Buying, roasting, labelling and pricing decaf for sale are on Decaf for a Small Roaster.
Children, teenagers and energy drinks

The American Academy of Pediatrics put its view in one sentence in 2011: caffeine and other stimulants in energy drinks “have no place in the diet of children and adolescents” (AAP clinical report). A review in Pediatrics the same year (Seifert and others) found that of 5,448 caffeine overdoses reported in the US in 2007, 46% were in people under 19. Children are smaller, so the same can is a bigger dose per kilogram, and energy drinks are often drunk quickly and cold.
For a coffee seller this has a practical side. A teenager ordering a large iced coffee with an extra shot is ordering 250 mg or more. Health Canada’s figure of 2.5 mg per kilogram puts a 50 kg (110 lb) teenager’s daily maximum at 125 mg. No US law sets an age for buying coffee, but a stall can choose to steer young customers to a small cup or a decaf. Hot drinks and children raise a second question, burns, covered on Serving Hot Drinks Safely.
A caffeine figure on the menu board is not required. The FDA requires added caffeine to appear in a packaged food’s ingredient list, but not the amount (FDA), and brewed coffee carries its caffeine naturally. A stall that does post a number should post a range (“a 12 oz cup: about 120 to 180 mg”) rather than a single figure, because the dose of coffee and the bean decide it.
Does coffee dehydrate you?
No, not at ordinary intakes. Caffeine makes the kidneys pass a little more water after a large dose, especially in someone not used to it, but a cup of coffee is mostly water and replaces more than it costs. The clearest test is a 2014 trial by Killer and colleagues: 50 men who habitually drank three to six cups a day spent three days drinking coffee (4 mg of caffeine per kilogram of body weight a day, about three to four 8 oz cups for an 80 kg man) and three days drinking the same volume of water. Measures of hydration did not differ, and the authors concluded that coffee “provides similar hydrating qualities to water.” The study was of habitual drinkers and of men only; it does not cover very large doses.
Medicines, blood pressure and the stomach
This section is not medical advice. It lists what published studies show so that a reader knows what to ask a doctor or pharmacist.
| Question | What the studies show |
|---|---|
| Medicines that slow caffeine down | The antidepressant fluvoxamine blocks CYP1A2, the enzyme that clears caffeine. In a 2005 trial it stretched caffeine’s half-life from 4.9 to 56 hours, so a daily coffee habit can build up. The antibiotic ciprofloxacin about doubled caffeine’s half-life (4.5 to 9.7 hours) in a 1992 study. Other drugs act on the same enzyme; a pharmacist can say which. |
| Thyroid medicine | Coffee and soy have “the greatest impact on the reduction of absorption” of levothyroxine among foods, in a 2017 review. The usual advice is to take the pill with water and wait before the morning coffee; the doctor or the pill’s leaflet gives the interval. |
| Iron | A cup of coffee with a hamburger meal cut the iron absorbed from it by 39% in a 1983 study. Coffee drunk an hour before the meal had no effect; an hour after, the same effect as with it. Someone short of iron can drink the coffee between meals. |
| Blood pressure | In people with high blood pressure, 200 to 300 mg of caffeine raised it by about 8/6 mm Hg for three hours or more, but in the longer trials habitual coffee did not raise it, and cohort studies found no higher heart-disease risk (Mesas and others, 2011). In the general population, one or two cups a day were not linked with developing high blood pressure, and three or more with slightly less of it (D’Elia and others, 2019). A blood-pressure reading taken soon after a coffee will read high. |
| Palpitations and heart rhythm | In the 2023 CRAVE trial, 100 adults were told by text message, day by day at random, to drink coffee or avoid caffeine. Coffee days brought no significant change in extra beats from the upper chambers, but more from the lower chambers: 154 against 102 premature ventricular contractions a day (Marcus and others, NEJM). Such beats are usually harmless and are felt as a skip or a thud. The UK Biobank study in the table above found coffee drinkers no more likely to develop arrhythmias. Anyone with a diagnosed rhythm problem should ask their cardiologist. |
| Heartburn and reflux | The evidence is mixed. A 2014 meta-analysis of fifteen studies found no significant link (odds ratio 1.06); a larger 2026 review of 40 studies found reflux slightly more common in coffee drinkers (34.9% against 30.7%) and called the effect of “unclear clinical significance.” A person whose heartburn follows coffee has their own answer; a lower-acid coffee is not proven to help, because cold brew and hot coffee have about the same pH (above). |
Withdrawal
Caffeine withdrawal is a recognised condition. A review of 66 studies by Juliano and Griffiths found:
| Feature | Finding |
|---|---|
| Most common symptom | headache, in about 50% |
| Others | tiredness, low energy, drowsiness, low mood, poor concentration, irritability, a “foggy” head; possibly flu-like aches and nausea |
| Starts | 12 to 24 hours after the last dose |
| Worst | 20 to 51 hours |
| Lasts | 2 to 9 days |
| Dose that can cause it | as little as 100 mg a day, about one cup |
The way to cut back without the headache is to step down over a week or two: mix in decaf, a quarter more each few days.
Corrections to common claims
More, beyond health, are on Coffee Myths and Corrections. The sweetener headlines (erythritol and blood clots, aspartame and cancer, both 2023) are read on Sugar-Free Sweeteners and Plant Milks.
| The claim | What the evidence says |
|---|---|
| ”Dark roast has more caffeine.” | Brewed the same way, dark roasts gave less in a 2024 study. The difference is small. |
| ”Espresso has the most caffeine.” | Per ounce, yes. Per drink, a single shot (about 64 mg) has less than an 8 oz drip coffee (about 95 mg). But café shots vary from 51 to 322 mg. |
| ”Cold brew is low-acid.” | Its pH matched hot coffee in a direct comparison. |
| ”Decaf has no caffeine.” | 2 to 15 mg a cup. |
| ”Coffee causes heart disease.” | The large studies find lower heart-disease death in moderate drinkers, after adjusting for smoking. Slow CYP1A2 metabolisers who drink 4+ cups are the possible exception. |
| ”Coffee prevents diabetes / Parkinson’s / liver disease.” | It is associated with less of each. Cause is not proven. |
| ”French press is healthier because nothing is filtered out.” | The opposite, for cholesterol: what the paper removes is what raises LDL. |
| ”Coffee carries a cancer warning in California.” | It did from 2018. Since 2019 the state’s own rule says it needs none. |
| ”Coffee dehydrates you.” | Not at ordinary intakes; it hydrated as well as water in a 2014 trial. |
Sources
- US Food and Drug Administration, Spilling the Beans: How Much Caffeine Is Too Much? (updated 28 August 2024).
- European Food Safety Authority, Caffeine (2015 scientific opinion).
- Health Canada, Caffeine in foods (updated 2 April 2025).
- Columbia University Irving Medical Center, Caffeine During Pregnancy (summarising ACOG Committee Opinion 462).
- USDA, FoodData Central — SR Legacy entries for brewed coffee, espresso, instant and decaf.
- Crozier, Stalmach, Lean and Crozier, Espresso coffees, caffeine and chlorogenic acid intake, Food & Function, 2012.
- Lindsey and others, Caffeine content in filter coffee brews as a function of degree of roast and extraction yield, Scientific Reports, 2024.
- Fuller and Rao, The effect of time, roasting temperature, and grind size on caffeine and chlorogenic acid concentrations in cold brew coffee, Scientific Reports, 2017.
- Temple and others, The Safety of Ingested Caffeine: A Comprehensive Review, Frontiers in Psychiatry, 2017.
- Drake, Roehrs, Shambroom and Roth, Caffeine Effects on Sleep Taken 0, 3, or 6 Hours before Going to Bed, Journal of Clinical Sleep Medicine, 2013.
- Nehlig, Interindividual Differences in Caffeine Metabolism, Pharmacological Reviews, 2018.
- Cornelis, El-Sohemy, Kabagambe and Campos, Coffee, CYP1A2 genotype, and risk of myocardial infarction, JAMA, 2006.
- Loftfield and others, Association of Coffee Drinking With Mortality by Genetic Variation in Caffeine Metabolism, JAMA Internal Medicine, 2018.
- Freedman and others, Association of coffee drinking with total and cause-specific mortality, NEJM, 2012.
- Poole and others, Coffee consumption and health: umbrella review, BMJ, 2017.
- Ding and others, Caffeinated and decaffeinated coffee consumption and risk of type 2 diabetes, Diabetes Care, 2014.
- Kennedy and others, Coffee consumption and the risk of cirrhosis, 2016; Coffee and the risk of hepatocellular carcinoma, BMJ Open, 2017.
- Ross and others, Association of coffee and caffeine intake with the risk of Parkinson disease, JAMA, 2000.
- Chieng and others, The impact of coffee subtypes on incident cardiovascular disease, arrhythmias, and mortality, European Journal of Preventive Cardiology, 2022.
- Urgert and Katan, The cholesterol-raising factor from coffee beans, Annual Review of Nutrition, 1997.
- van Dusseldorp and others, Cholesterol-raising factor from boiled coffee does not pass a paper filter, 1991.
- Zhang, Linforth and Fisk, Cafestol extraction yield from different coffee brew mechanisms, Food Research International, 2012.
- Moeenfard and others, Diterpenes in espresso coffee: impact of preparation parameters, 2015.
- Svatun and others, Association between espresso coffee and serum total cholesterol: the Tromsø Study, Open Heart, 2022.
- Tverdal and others, Coffee consumption and mortality: does the brewing method matter?, European Journal of Preventive Cardiology, 2020.
- Scali Rasmussen, Coffee and Prop 65: The long and winding road is over, 25 April 2023.
- European Union, Regulation 2017/2158 (acrylamide benchmarks); Regulation 2023/915 (contaminant maximums); Directive 1999/4/EC (coffee and chicory extracts).
- 21 CFR 173.255, methylene chloride (Cornell Legal Information Institute).
- Page and Charbonneau, Headspace gas chromatographic determination of methylene chloride in decaffeinated tea and coffee, Journal of the AOAC, 1984.
- Center for Science in the Public Interest, EPA banned methylene chloride, but it’s still used in foods, May 2024.
- Daily Coffee News, FDA Weighs Next Steps on Decaf Solvent Rules, 30 June 2026.
- Barista Magazine, Will the FDA Ban Methylene Chloride in Decaf Coffee?, 27 July 2026.
- CalMatters Digital Democracy, AB 2066.
- Killer, Blannin and Jeukendrup, No Evidence of Dehydration with Moderate Daily Coffee Intake, PLOS ONE, 2014.
- Culm-Merdek and others, Fluvoxamine impairs single-dose caffeine clearance, British Journal of Clinical Pharmacology, 2005; Mahr and others, Effects of temafloxacin and ciprofloxacin on the pharmacokinetics of caffeine, Clinical Pharmacokinetics, 1992.
- Skelin and others, Factors Affecting Gastrointestinal Absorption of Levothyroxine, Clinical Therapeutics, 2017.
- Morck, Lynch and Cook, Inhibition of food iron absorption by coffee, American Journal of Clinical Nutrition, 1983.
- Mesas and others, The effect of coffee on blood pressure and cardiovascular disease in hypertensive individuals, AJCN, 2011; D’Elia and others, Coffee consumption and risk of hypertension, European Journal of Nutrition, 2019.
- Marcus and others, Acute Effects of Coffee Consumption on Health among Ambulatory Adults, NEJM, 2023.
- Kim and others, Association between coffee intake and gastroesophageal reflux disease, Diseases of the Esophagus, 2014; Muftah and others, Association of Coffee Intake With Risk of Gastroesophageal Reflux Disease, Clinical and Translational Gastroenterology, 2026.
- US EPA, Risk Management for Methylene Chloride; California OEHHA, Proposition 65; IARC.
- Swiss Water, The decaffeination process.
- Café du Monde, Frequently asked questions.
- Juliano and Griffiths, A critical review of caffeine withdrawal, Psychopharmacology, 2004.
- American Academy of Pediatrics, Sports drinks and energy drinks for children and adolescents, Pediatrics, 2011; Seifert and others, Health effects of energy drinks, Pediatrics, 2011.
Comments (0)